
Delayed presentation of intracameral graphite foreign body in a child: school trauma
阅读量:1425
DOI:doi: 10.3978/j.issn.1000-4432.2016.09.03
发布日期:2024-11-30
作者:
Brijesh Takkar ,Shorya Vardhan Azad
展开更多 
关键词
Graphite foreign body
intraocular foreign body in children
school trauma
摘要
We report a case of large graphite foreign body (FB) in the anterior chamber of eye of a 4-yearold
child, incurred during unsupervised play. Despite delayed presentation, the eye had few signs of resolved
inff ammation which allowed safe extraction of the FB bimanually through limbus. School play, especially in
young children, should be under supervision and free of sharp objects. Graphite is inert while inside the eye,
and even large pieces can be well tolerated for long time in absence of infection.
全文
Case presentation
We report a case of a 4-year-old girl child who was presented
to our ocular emergency department with blurred vision in
left eye (LE). There was history of trauma in school with a
graphite based pencil 21 days back. Trauma had occurred
while playing in class room and delayed presentation was
due to late referral and economic reasons. Child did not
allow complete examination or accurate assessment of visual
acuity. However, supersonic inspection of the LE posterior
segment was found to be normal. Hence keeping a suspicion
of open globe injury, parents were counseled for examination
under anesthesia and possible surgery for primary repair in
operation room. A written informed consent was obtained
from the parents for the surgery. During examination under
anesthesia, right eye was within normal limits while LE
was found to have a full thickness corneal laceration in the
inferonasal quadrant along with a large piece of pencil lead
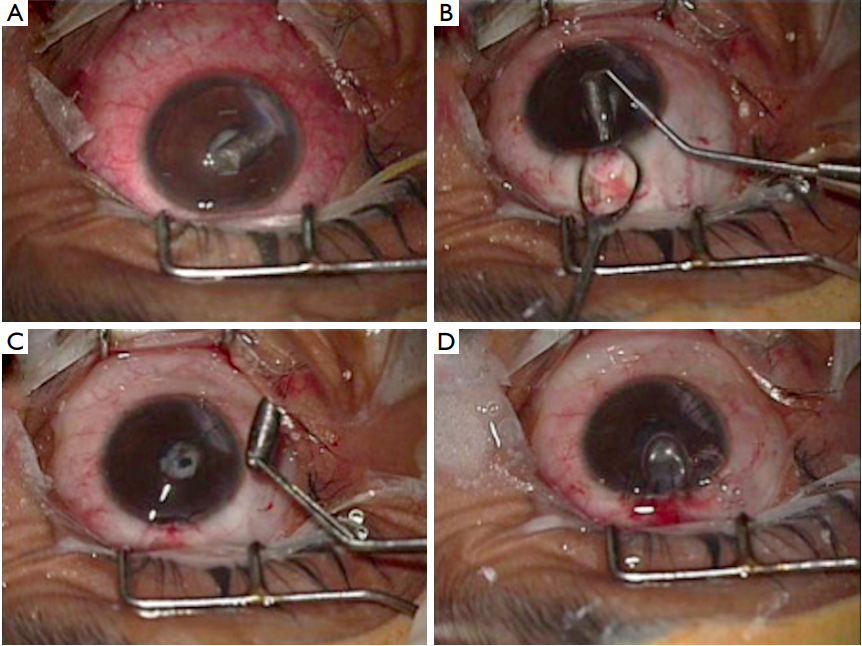
in anterior chamber and cataract (Figure 1A). The pencil lead
was more than half the size of the corneal diameter. There
were no gross signs of inff ammation.
The wound was secured with a single 10–0 mono filament nylon suture and the anterior chamber formed with visco-elastic. A superior limbal incision was made and the long axis of foreign body (FB) was aligned perpendicular to it. The FB was delivered bimanually using a hook and a non-irrigating wire Vectis (Figure 1B). The laceration and superior incision were then repaired and anterior chamber formed with air and saline (Figure 1C,D). Multiple long sutures were needed to repair the wound. The anterior chamber was well formed, intra ocular pressure normal on digital palpation with visual acuity of counting ff ngers close to face on ff rst postoperative day. She subsequently underwent lens aspiration with intraocular lens implant 6 weeks later, and her visual acuity improved to at least 6/18.
The wound was secured with a single 10–0 mono filament nylon suture and the anterior chamber formed with visco-elastic. A superior limbal incision was made and the long axis of foreign body (FB) was aligned perpendicular to it. The FB was delivered bimanually using a hook and a non-irrigating wire Vectis (Figure 1B). The laceration and superior incision were then repaired and anterior chamber formed with air and saline (Figure 1C,D). Multiple long sutures were needed to repair the wound. The anterior chamber was well formed, intra ocular pressure normal on digital palpation with visual acuity of counting ff ngers close to face on ff rst postoperative day. She subsequently underwent lens aspiration with intraocular lens implant 6 weeks later, and her visual acuity improved to at least 6/18.
Figure 1 Intraoperative removal of foreign body. (A) Full thickness corneal laceration along with intra cameral graphite foreign body (FB). Note sharp end of FB is towards the wound; (B) wound repaired with single suture and FB being removed bimanually with sinskey hook and wire Vectis; (C) FB successfully removed without complications; (D) wound and incision site repaired with nylon sutures and anterior chamber formed with air bubble.
Discussion
School trauma during unsupervised play is common and
can be blinding (1). Such children are especially prone to
trauma with sharp objects like pencils which are commonly
available in the school premises. Unsupervised play with
sharp objects should therefore be avoided. Penetrating
injuries may present with lack of pain or redness or pertinent
history, especially in less than 5 years age group and should
not stop us from suspicion of a FB. One ff fth of patients with
ocular FB may present without any symptoms (2). Although
superficial FB on the conjunctiva or cornea may be easily
seen and at times managed in the emergency room itself,
supratarsal and intraocular FB may require specialized slit
lamp examination and expert surgical removal. Appropriate
referral should be made as early as possible for the same as delayed management increases the possibility of vision
threatening complications like endophthalmitis (3).
Graphite being inert does not incite inflammatory reactions (4), unless infective, explaining a relatively stable anterior chamber. The only evidence of previous inflammation in our case was a thin membrane over the pupil, which was easily removed. The eye overall appeared to be stable at presentation, notwithstanding the size of the FB or prolonged exposure to graphite. Wound apposition however was difficult, presumably due to delayed repair. Orienting the long axis of FB perpendicular to the removal site (Figure 1B) followed by bimanual extraction is easy and off ers an uncomplicated removal of large anterior chamber foreign bodies.
Graphite being inert does not incite inflammatory reactions (4), unless infective, explaining a relatively stable anterior chamber. The only evidence of previous inflammation in our case was a thin membrane over the pupil, which was easily removed. The eye overall appeared to be stable at presentation, notwithstanding the size of the FB or prolonged exposure to graphite. Wound apposition however was difficult, presumably due to delayed repair. Orienting the long axis of FB perpendicular to the removal site (Figure 1B) followed by bimanual extraction is easy and off ers an uncomplicated removal of large anterior chamber foreign bodies.
Conclusions
School trauma is a cause of preventable vision loss in young
children and school environment needs to be appropriately
controlled. Intraocular graphite FB is well tolerated, though
delayed wound repair may be difficult.
基金
暂无基金信息
参考文献
1. Ayanniyi AA, Mahmoud OA, Olatunji FO, et al. Pattern of ocular trauma among primary school pupils in Ilorin, Nigeria. Afr J Med Med Sci 2009;38:193-6.
2. Upshaw JE, Brenkert TE, Losek JD. Ocular foreign bodies in children. Pediatr Emerg Care 2008;24:409-14; quiz 415-7.
3. Li X, Zarbin MA, Bhagat N. Pediatric open globe injury: A review of the literature. J Emerg Trauma Shock 2015;8:216-23.
4. Han ER, Wee WR, Lee JH, et al. A case of retained graphite anterior chamber foreign body masquerading as stromal keratitis. Korean J Ophthalmol 2011;25:128-31.