Ocular surface squamous neoplasia (OSSN) is the most common tumor of the ocular surface, including squamous cell papilloma, actinic keratosis, conjunctival intraepithelial neoplasia and squamous cell carcinoma. The extended understanding of clinicopathological features could help improve clinical accurate diagnosis of these lesions. This article reviews the classification, clinical features and pathological characteristics of OSSN to provide the reference for clinical diagnosis and treatment.
Article
眼球表面鳞状细胞性肿瘤(oc lar surface squamous neoplasia,OSSN)指起源于结膜或角膜表面鳞状上皮细胞的一组上皮性肿瘤[1-3]。从病理学角度,OSSN包括鳞状细胞乳头状瘤、上皮内瘤变、日光性角化病和鳞状细胞癌等多种肿瘤。因此OSSN是对结膜或角膜上皮性肿瘤的一个概括性临床诊断用语,而不是一个确切的病理诊断。尽管这组肿瘤在病因学方面有很多相关性,但每一种病变都具有不同的临床病理学特点和生物学行为。临床上OSSN并不少见,尤其角结膜缘部位是最常好发部位。因此,充分了解这些病变的组织发生、临床表现和病理学特点有助于提高对不同类型病变的认识和治疗方案的选择,提高临床治疗的效果。
1 鳞状细胞乳头状瘤
1.1 病因和临床表现
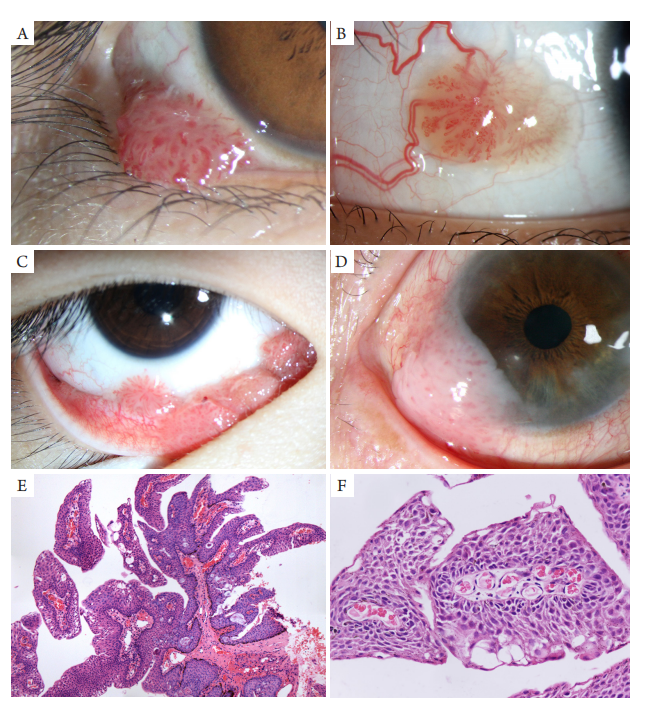
鳞状细胞乳头状瘤(squamous papilloma of conjunctiva)属于良性上皮性肿瘤,组织起源于结膜或角膜缘的上皮细胞。文献[4]中报道部分病例可能与人类乳头状瘤6型或1 1型病毒感染有关。本瘤可发生于任何年龄,多见于中青年人,好发于睑缘、内眦部、角结膜缘或球结膜。肿瘤一般呈单发性病灶,向结膜表面外生性生长,呈肉红色或粉红色的乳头状或菜花状,其内可见细小的血管襻。睑缘或内眦部的鳞状细胞乳头状瘤常呈桑葚状或息肉状、体积较小、有蒂;而球结膜或角结膜缘部位的鳞状细胞乳头状瘤常呈扁平状、基底比较广泛(图1),这可能是由于眼睑覆盖在肿瘤表面,从而限制了瘤体的生长。有些肿瘤蒂较窄,除与角结膜缘粘连外,游离部分的瘤体可向前覆盖在角膜上皮表面,但与角膜上皮无明显粘连。多灶性结膜乳头状瘤比较少见,好发于睑结膜或穹隆部结膜,多见于儿童或青少年患者。
(A) A pink papilloma arising from lower eyelid margin; (B) A solitary and sessile papilloma in bulbar conjunctiva, with markedly dilated feeder vessels; (C) Multiple and separate conjunctival papilloma arising from bublar and forniceal conjunctiva; (D) A pink papilloma with smooth surface at nasal limbus; (E) Pathological futures of squamous papilloma at eyelid margin, the tumor cells arranged in longer or short fronds with fibrovascular cones (HE, ×40); (F) Higher magnification photomicrograph shows fibrovascular cones within acanthotic epithelium (HE, ×200).
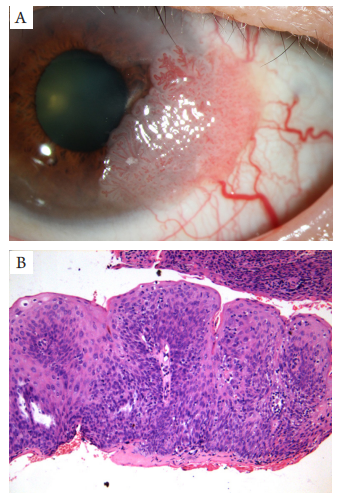
(A) Larger and pink sessile tumor arising from limbus, with markedly dilated feeder vessels; (B) Pathological section shows squamous papilloma with severe dysplasia, but the epithelial basement membrane was intact (HE, ×200).
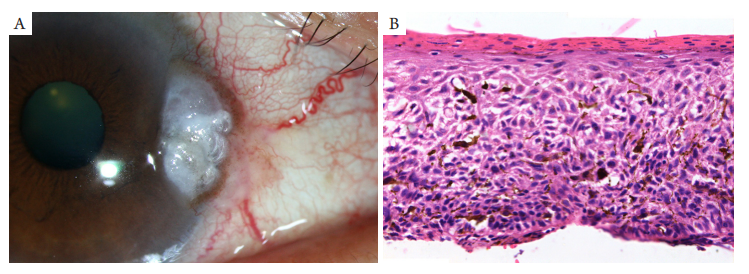
结膜日光性角化病(actinic keratosis of conjunctiva)好发于成年人睑裂部位的角结膜缘,其发生可能与长期日光照射有关,有些病例可发生于结膜慢性炎症、翼状胬肉或睑裂斑的表面。相关研究显示大多数日光性角化病中,P53蛋白过表达,其表达程度与细胞非典型增生的程度相关,P53蛋白聚集可能是由于P53基因突变的结果[7]。本病属于癌前病变,少数病例可发展为浸润性鳞状细胞癌。最近有学者[7-8]报道18例结膜日光性角化病的HPV检测均为阴性,提示HPV感染可能不是本病的致病因素。
(A) A flat and white plaque at temporal limbus in the interpalpebral region, with dilated vessels and minimal pigmentation; (B) Pathological section shows acanthosis, acantholysis, parakeratosis and dysplasia of conjunctival epithelium, with a few of dendritic melanocytes (HE,×200).
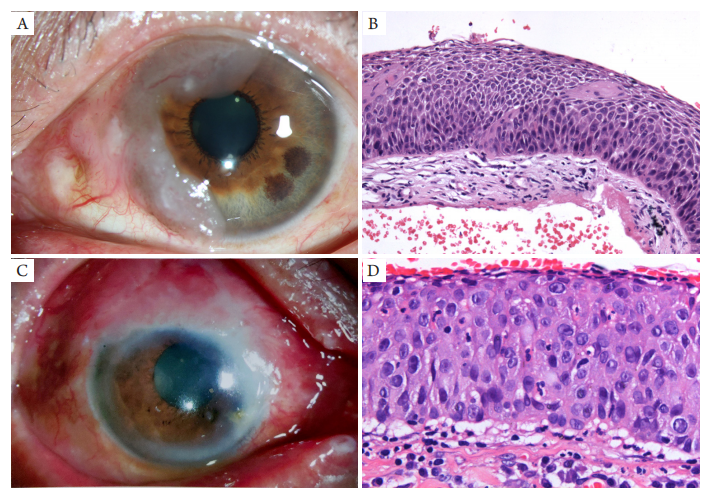
(A,B) A fleshy, flat and diffuse leukoplakia at nasal limbus and corneal periphery, the pathological section shows high-class CIN, full-thickness replacement of the epithelium by anaplastic cells, but basement membrane was intact (HE, ×200); (C,D) Diffffuse and minimally elevated pink tumor at limbus, simulating severe conjunctivitis, the pathological section of the excisional biopsy shows high-class CIN (HE,×400).
Margo CE, White AA. Ocular surface squamous neoplasia: terminology
that is conceptually friendly but clinically perilous[ J]. Eye (Lond),
2014, 28(5): 507-509.
Shields CL, Shields JA. Tumors of the conjunctiva and cornea[ J].
Indian J Ophthalmol, 2019, 67(12): 1930-1948.
Theotoka D, Morkin MI, Galor A, et al. Update on diagnosis and
management of conjunctival papilloma[ J]. Eye Vis (Lond), 2019, 6: 18.
Singh M, Gautam N, Gupta A , et al. Interferon alfa-2b in the
management of recurrent conjunctival papillomatosis[ J]. Indian J
Ophthalmol, 2016, 64(10): 778-780.
Rudkin AK, Dempster L, Muecke JS. Management of diffuse ocular
surface squamous neoplasia: efficacy and complications of topical
chemotherapy[ J]. Clin Exp Ophthalmol, 2015, 43(1): 20-25.
王玉川, 陈陆霞, 李静, 等. 结膜日光性角化病的临床病理学特点
及其与HPV的关系[ J]. 中华眼科杂志, 2019, 55(7): 531-535.
WANG YC, CHEN LX, LI J, et al. The clinicopathological
features and HPV detection of conjunctival actinic keratosis[ J].
Chinese Journal of Ophthalmology, 2019, 55(7): 531-535.
Shields JA, Shields CL. Eyelid, conjunctival, and orbital tumors:
an Atlas and textbook[M]. 2nd ed. St. Walnut: Philadelphia, 2008:
284-285.
Karp CL, Mercado C, Venkateswaran N, et al. Use of high-resolution
optical coherence tomography in the surgical management of ocular
surface squamous neoplasia: a pilot study[ J]. Am J Ophthalmol, 2019,
206: 17-31.
Shah SU, Kaliki S, Kim HJ, et al. Topical interferon alfa-2b for
management of ocular surface squamous neoplasia in 23 cases:
outcomes based on A mer ican Joint Committee on Cancer
classification[ J]. Arch Ophthalmol, 2012, 130(2): 159-164.
Parrozzani R, Frizziero L, Trainiti S, et al. Topical 1% 5-fluoruracil as a
sole treatment of corneoconjunctival ocular surface squamous neoplasia:
long-term study[ J]. Br J Ophthalmol, 2017, 101(8): 1094-1099.
Galor A, Karp CL, Oellers P, et al. Predictors of ocular surface
squamous neoplasia recurrence after excisional surger y[ J].
Ophthalmology, 2012, 119(10): 1974-1981.
Chalkia AK, Bontzos G, Spandidos DA, et al. Human papillomavirus
infection and ocular surface disease (Review)[ J]. Int J Oncol, 2019,
54(5): 1503-1510.
Santoni A, Thariat J, Maschi C, et al. Management of invasive
squamous cell carcinomas of the conjunctiva[ J]. Am J Ophthalmol,
2019, 200: 1-9.
Midena E, Angeli CD, Valenti M, et al. Treatment of conjunctival
squamous cell carcinoma with topical 5-fluorouracil[ J]. Br J Ophthalmol,
2000, 84(3): 268-272.
Venkateswaran N, Mercado C, Galor A, Karp CL. Comparison of
topical 5-fluorouracil and interferon alfa-2b as primary treatment
modalities for ocular surface squamous neoplasia[ J]. Am J Ophthalmol,
2019, 199: 216-222.
Arepalli S, Kaliki S, Shields CL, et al. Plaque radiotherapy in the
management of scleral-invasive conjunctival squamous cell carcinoma:
an analysis of 15 eyes[ J]. JAMA Ophthalmol, 2014, 132(6): 691-696.